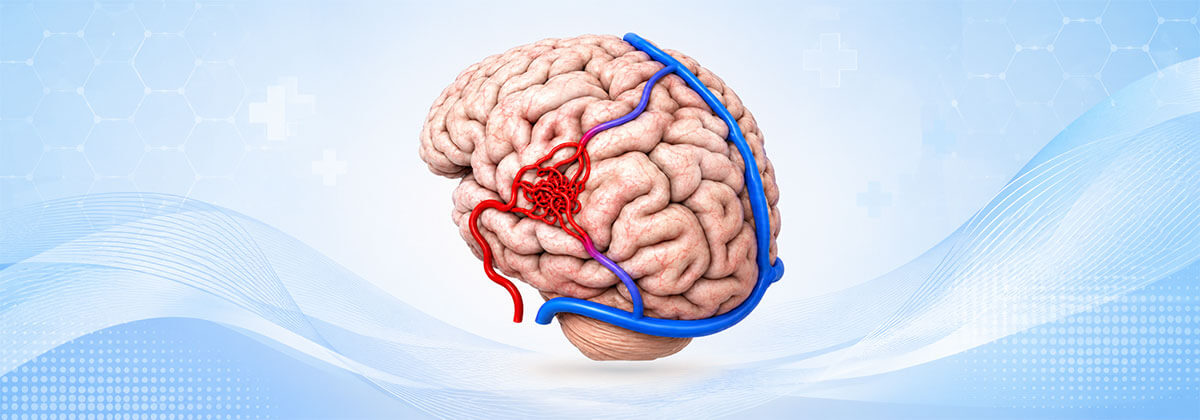
Arteriovenous Malformations (AVMs)
An Arteriovenous Malformation (AVM) is a complex, abnormal tangle of blood vessels connecting arteries and veins in the brain or spinal cord. Because AVMs bypass the normal capillary bed that slows blood flow, high-pressure arterial blood flows directly into delicate veins, exposing them to rupture, intracranial hemorrhage, or neurological deficits. Dr. Pradyumna Oak provides expert clinical evaluation, risk stratification, and comprehensive neurointerventional management for brain and spinal AVMs.
Using high-resolution vascular imaging and advanced endovascular embolization techniques, Dr. Oak develops individualized treatment strategies to safely block abnormal blood vessels, prevent catastrophic bleeding, control symptoms like seizures and severe headaches, and protect long-term brain function.
What is an Arteriovenous Malformation (AVM)?
An Arteriovenous Malformation is a congenital vascular anomaly where high-pressure arteries connect directly to low-pressure veins without an intervening capillary network. This central tangle of abnormal vessels—known as the nidus—causes high-volume, high-velocity blood shunting that can weaken vessel walls, lead to aneurysm formation on feeding arteries, or restrict normal oxygenated blood flow to surrounding brain tissue (steal phenomenon).
Treatment for AVMs ranges from conservative monitoring to targeted interventions like Endovascular Embolization—a minimally invasive procedure where microcatheters deliver specialized liquid embolic agents (such as Onyx or liquid glues) into the nidus to shut down the abnormal blood flow and eliminate or significantly reduce rupture risk.
Conditions & Scenarios We Evaluate & Treat
Our specialized neurointerventional practice offers comprehensive assessment and management across the full spectrum of vascular malformations, including:
Unruptured Brain AVMs
In-depth clinical risk assessment, Spetzler-Martin grading, and preventive treatment planning for asymptomatic or symptom-causing intact AVMs.
Ruptured Brain Aneurysms / AVM Hemorrhage
Emergency medical stabilization, triage, and urgent endovascular or surgical management following intracranial or subarachnoid hemorrhage.
Spinal Arteriovenous Malformations & Fistulas
Specialized diagnosis and targeted embolization of abnormal vascular connections in and around the spinal cord causing progressive leg weakness or sensory loss.
Dural Arteriovenous Fistulas (dAVFs)
Evaluation and endovascular closure of direct connections between dural arteries and venous sinuses near the brain's covering layer.
Plexiform & High-Flow AVMs
Staged endovascular embolization procedures designed to reduce large nidus volume prior to surgical resection or stereotactic radiosurgery.
AVM-Associated Arterial Aneurysms
Targeted treatment of high-risk flow-related aneurysms that form on feeding arteries due to increased hemodynamic stress.
AVM-Related Seizures & Epilepsy
Comprehensive neurological management and anti-seizure medication optimization for patients experiencing seizures caused by AVM cortical irritation.
Pediatric Vascular Malformations
Multidisciplinary evaluation and long-term surveillance for children and young adults diagnosed with congenital cerebral vascular malformations.
Symptoms You Should Never Ignore
While some AVMs remain silent until a rupture occurs, others produce warning symptoms due to pressure or tissue hypoxia. Seek immediate medical evaluation if you experience:
- Sudden, severe, localized, or persistent headaches
- Sudden onset of seizures or convulsions (generalized or partial)
- Progressive muscle weakness, paralysis, or numbness in the face, arms, or legs
- Difficulty speaking, slurred speech, or trouble understanding language (aphasia)
- Sudden vision loss, blurred vision, double vision, or visual field deficits
- Dizziness, loss of balance, or unsteadiness while walking
- Pulsatile tinnitus (hearing a rhythmic swooshing or thumping sound in the ears matching the heartbeat)
- Memory loss, confusion, or progressive cognitive decline
- Back or neck pain radiating down the legs with progressive weakness (spinal AVM signs)
A sudden "thunderclap" headache, seizure, or acute neurological deficit requires immediate emergency care to check for bleeding.
Our Diagnostic Approach
Precise mapping of the AVM architecture, feeder vessels, and venous drainage routes is fundamental for safe treatment planning. Diagnostic evaluation includes:
- Comprehensive neurological examination and functional risk evaluation
- Emergency Non-Contrast CT Scan (to detect acute hemorrhage or calcifications)
- High-resolution CT Angiography (CTA) for 3D vascular reconstruction
- Brain MRI and MR Angiography (MRA) to map surrounding eloquent brain tissue
- Digital Subtraction Angiography (DSA) — the gold standard gold diagnostic tool for evaluating arterial feeders, nidus flow dynamics, and venous outflow
- Functional MRI (fMRI) or SPECT imaging to preserve language and motor centers prior to intervention
- Multidisciplinary case review (Spetzler-Martin grading scale classification)
Every imaging modality is selected to provide a complete structural roadmap of the malformation before any intervention is recommended.
Personalized Treatment Plans
AVM treatment is tailored to the individual based on lesion location, size, venous drainage type, rupture history, and overall patient health. Management options include:
- Endovascular Embolization (using liquid embolic agents like Onyx/Squid to close off feeding arteries and the nidus)
- Multimodality Therapy (Combining pre-operative embolization with microsurgical resection or radiosurgery)
- Referral and coordination for Stereotactic Radiosurgery (Gamma Knife / CyberKnife) for small or deep-seated AVMs
- Conservative clinical surveillance and MRI monitoring for low-risk or high-complexity lesions
- Anti-seizure medication management for symptom control
- Post-procedure neuro-ICU monitoring and strict blood pressure control
- Rehabilitation guidance (physical, speech, and occupational therapy) for recovery post-rupture
- Long-term angiographic follow-up to confirm permanent obliteration
Book an Appointment
If you or a loved one have been diagnosed with an AVM, are experiencing unexplained seizures, severe headaches, or pulsating head noises, early expert evaluation is essential. Comprehensive neurovascular assessment helps clarify your risk profile and outlines the safest treatment path.
Schedule your consultation with Dr. Pradyumna Oak today for expert AVM evaluation and neurointerventional care.
Frequently Asked Questions (FAQs)
Find answers to common questions about Arteriovenous Malformations (AVMs) and endovascular embolization.